
Telemedicine for Rural Eye Care

An eye test at the local pharmacy, with a specialist a video call away.
Rural patients often live far from an eye specialist, and a video call can’t test their eyes. Over a month at Indiana University, our team of five designed Eye Care Connect: a kiosk in the local pharmacy, where the pharmacist runs the eye tests and connects patients to a remote specialist when they need one.
I worked on product design and research. I ran some of our interviews and the secondary research, built the affinity map with the team, designed the kiosk’s wireframes end to end, and ran usability testing.
Product design & research
1 month, 2023
Sriram Hemanth Kumar
Rutuja Patil
Monisha Vimal Mansukhani
Zainab Hassani
Nikita Juriasinghani
Figma
Photoshop
Miro
Google Docs
Bill’s world
Our story has two main characters, drawn from our persona and storyboard.
Bill
55, a farmer in rural Indiana
Two weeks of blurry vision and headaches, and the nearest specialist is too far and too costly to reach.

The pharmacist
The kiosk technician
Already part of Bill’s week. In our design, the pharmacist runs the kiosk and calls in a specialist when needed.
Bill’s problem isn’t rare. In rural America, getting to a doctor takes longer, and eye specialists are often not there at all.
27 min
Average trip to a primary care doctor for rural adults over 50, against 19 minutes in cities. A specialist is usually further.
Source: JAMA Network Open, 202562.7%
of US counties had no practicing ophthalmologist in 2021, up from 60.7% in 2010, and most of them are rural.
Source: Graefe’s Archive for Clinical and Experimental Ophthalmology, 2026The call
Our class, INFO I541 Introduction to HCI/d, took on the CHI 2024 Student Design Competition brief, anchored on the UN’s Sustainable Development Goal 3: good health and well-being. We chose eye care in rural areas, where the gap in access is widest.
How might we
bring eye care to rural patients like Bill, in a way that’s affordable, sustainable and accessible, without asking them to travel to a specialist?
What we heard
We read the research on rural health, telemedicine and remote vision testing, then interviewed people about how they get eye care today. Their answers came down to two barriers and one wish.
Getting there
- Long waits, in cities and in the country alike
- Appointments are hard to fit around family
- A long journey is reason enough not to go
Trusting it
- Telemedicine felt like it lacked a personal touch
- People doubted a test done through a screen was accurate
- Serious eye injuries still need someone in the room
Wanting it
- Everyone we spoke to was keen on telemedicine
- Virtual check-ups and follow-ups felt convenient
- Flexible appointments mattered most
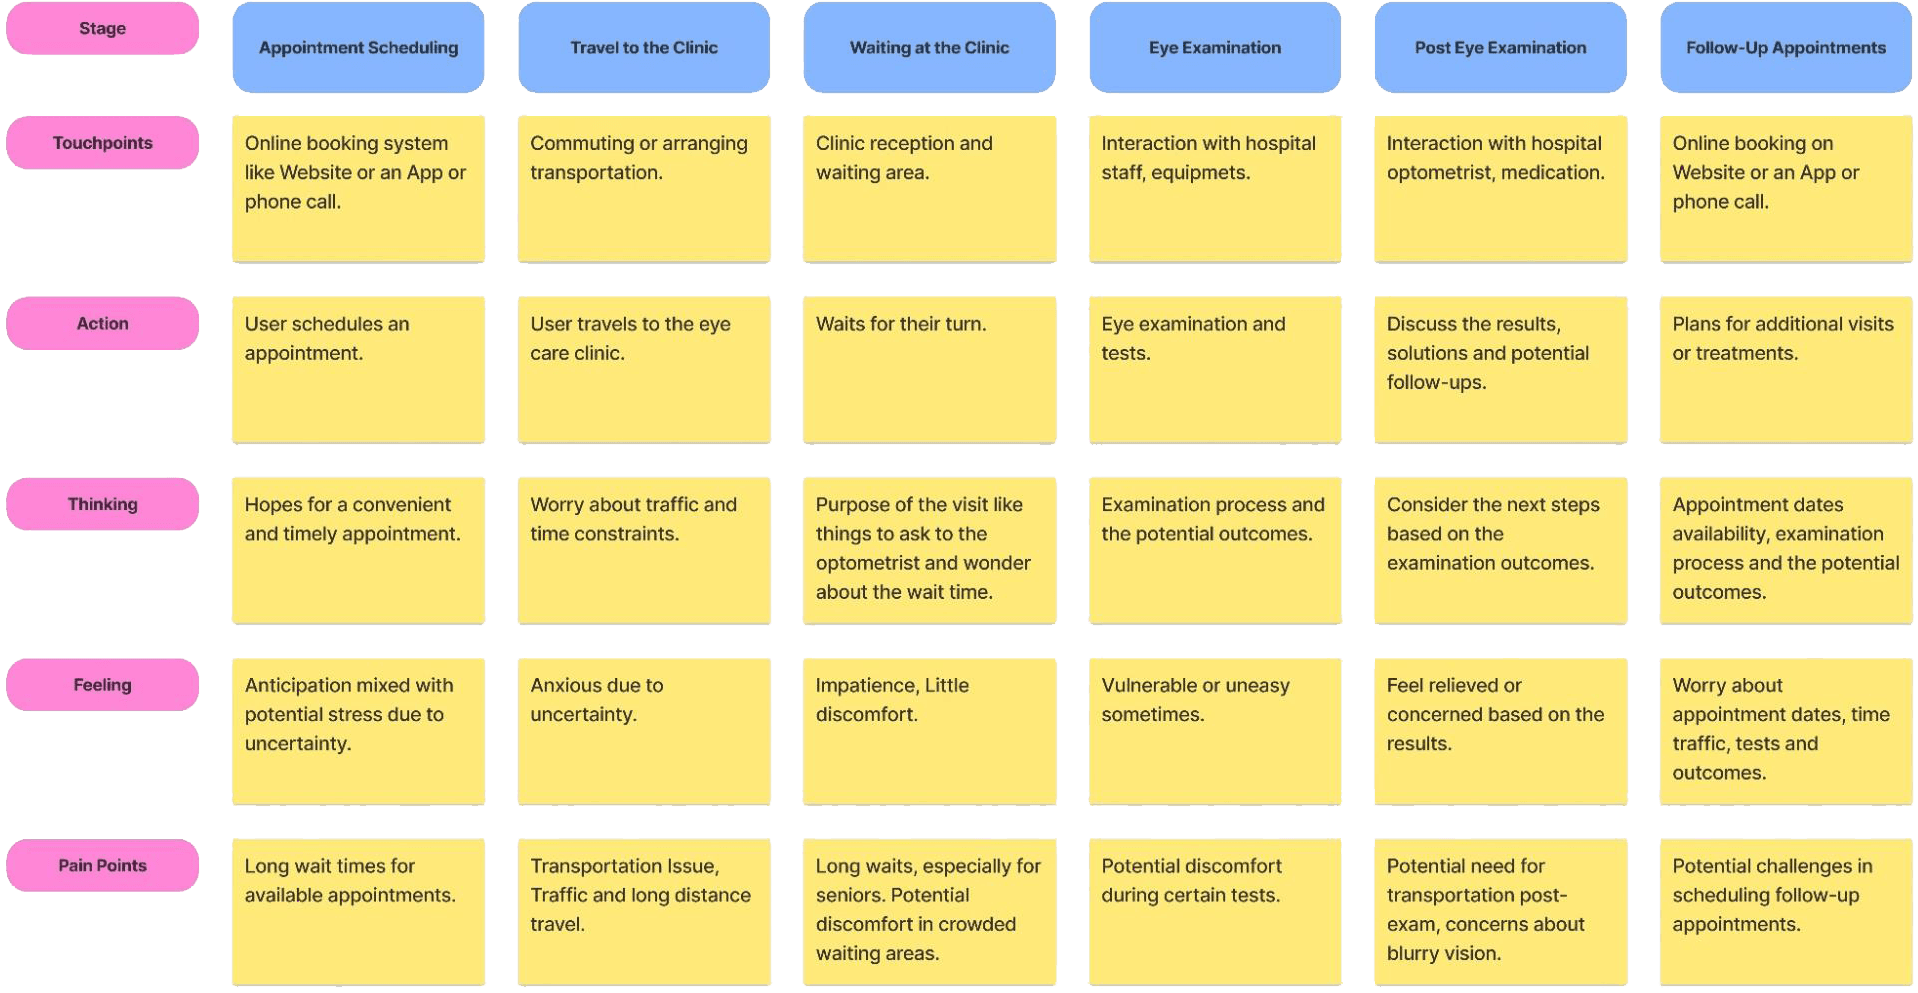
We mapped a patient’s eye care visit end to end, from scheduling to follow-up
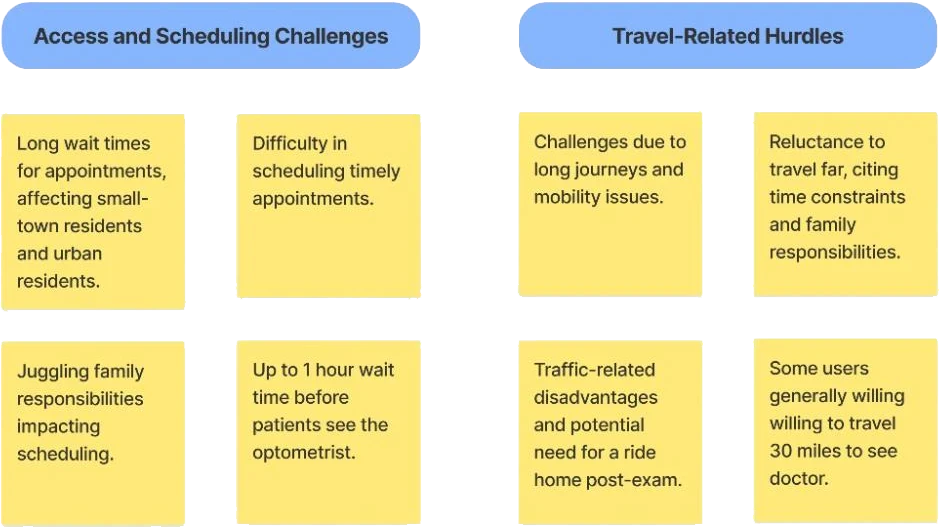
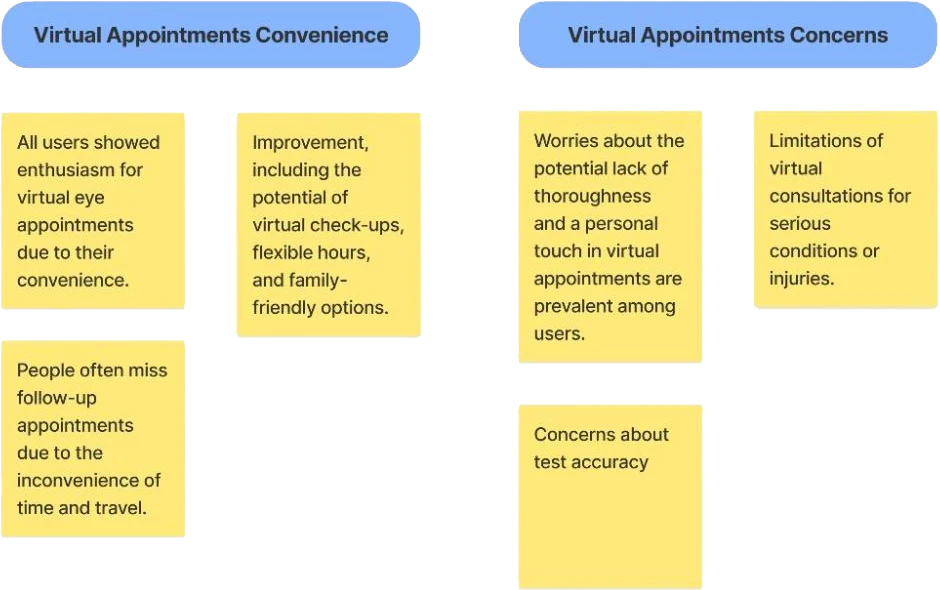

Then clustered what we heard on an affinity map
Four ideas
We sketched four ways to bring the test to Bill. Each solved part of what we heard. We settled on a kiosk, then weighed a booth of several machines against a single kiosk before choosing the last.
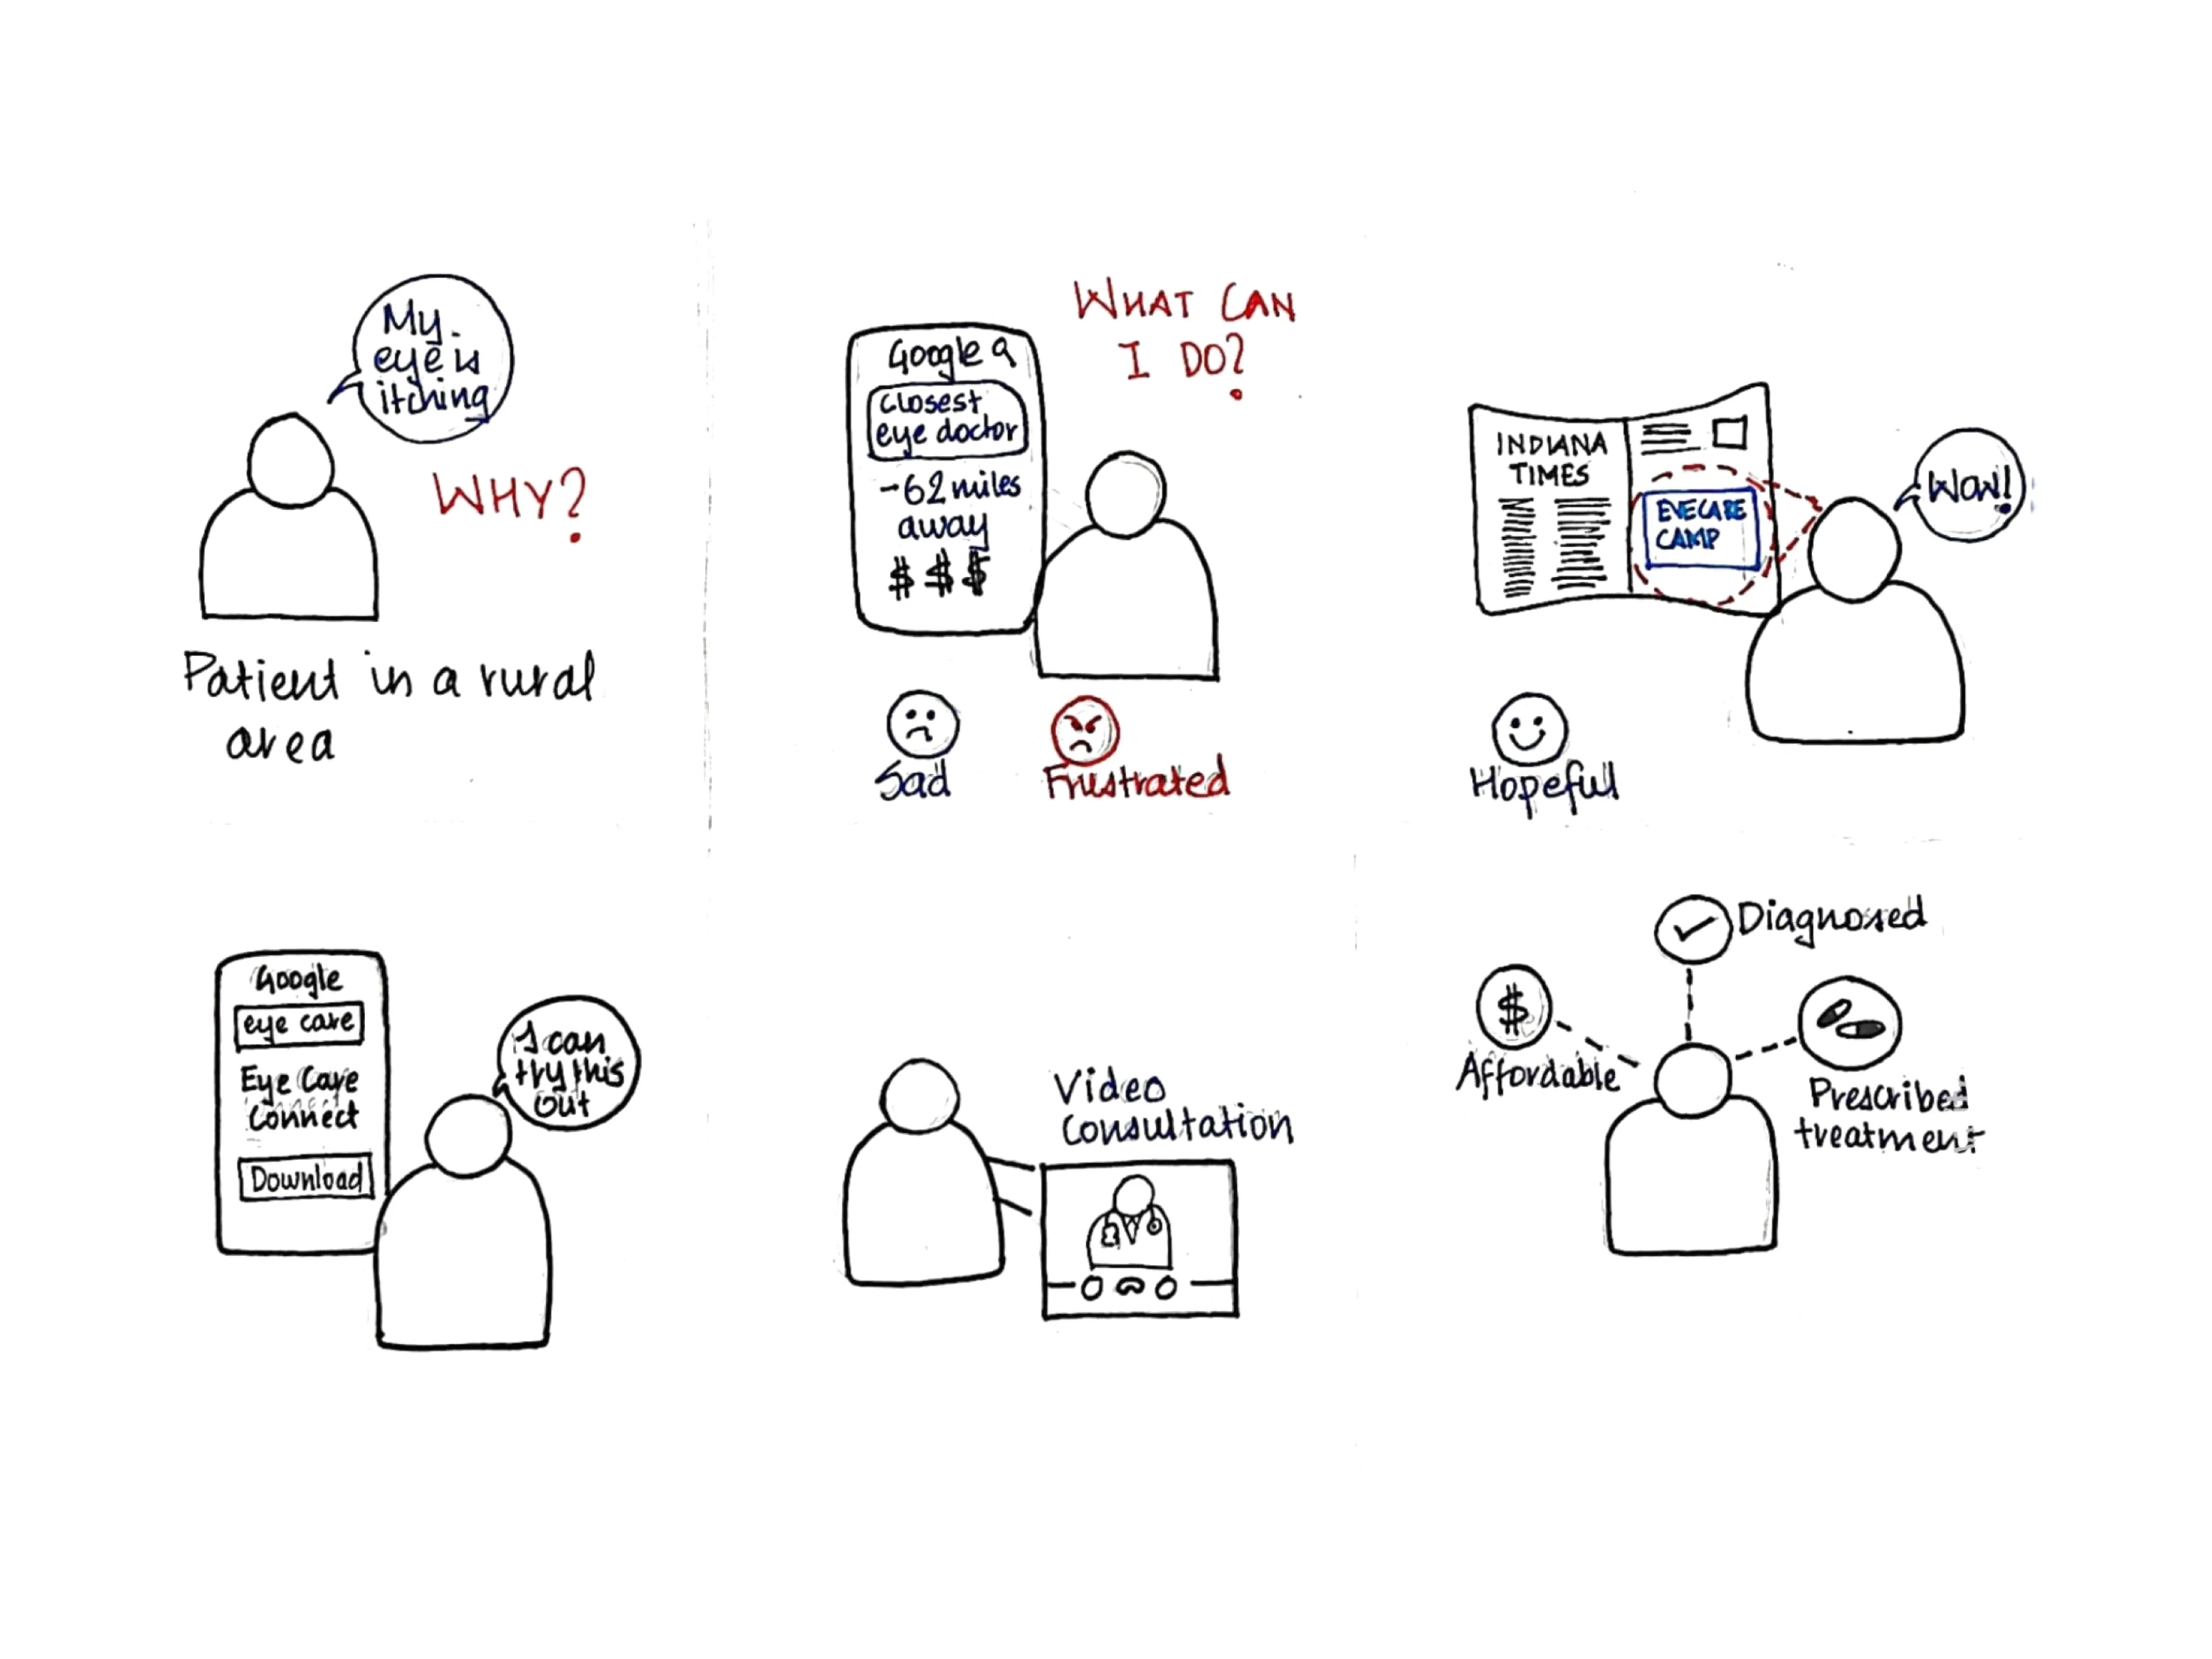
Home kit and app
No travel at all: a self-test kit and an app at home.
Bill tests alone, the very thing people doubted.
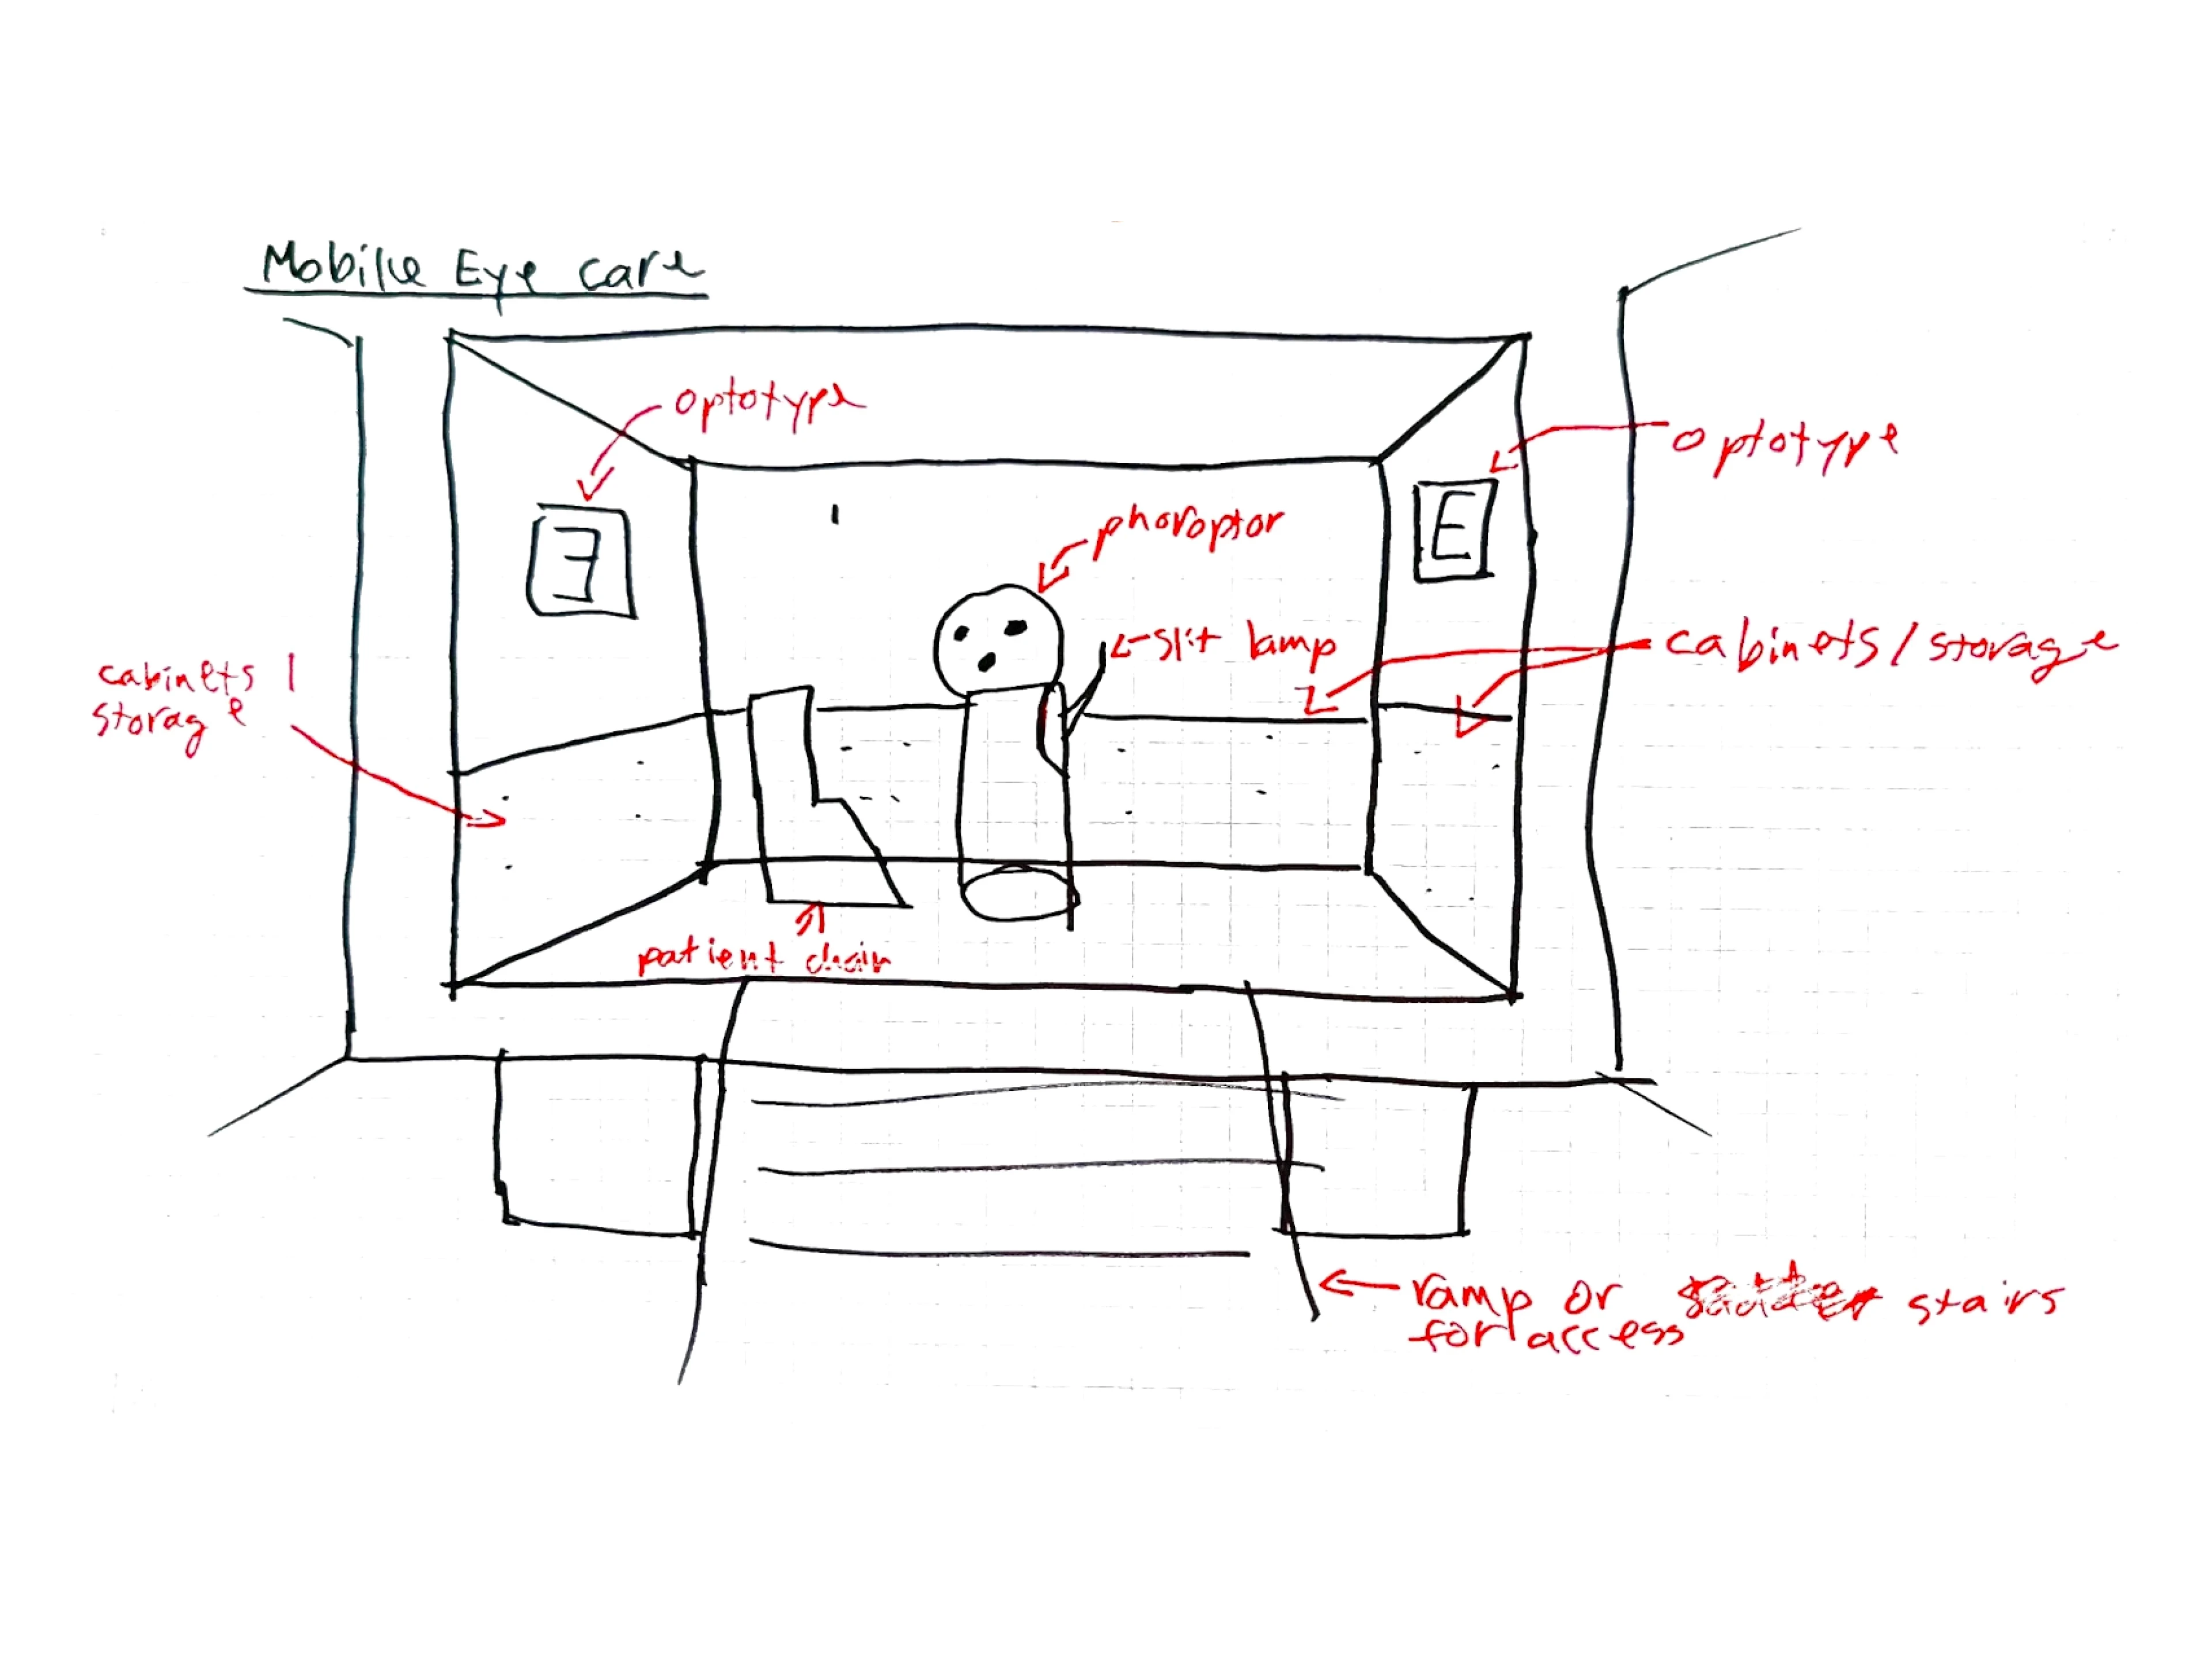
Mobile eye van
In-person care that comes to town.
Care only on the days the van is there.
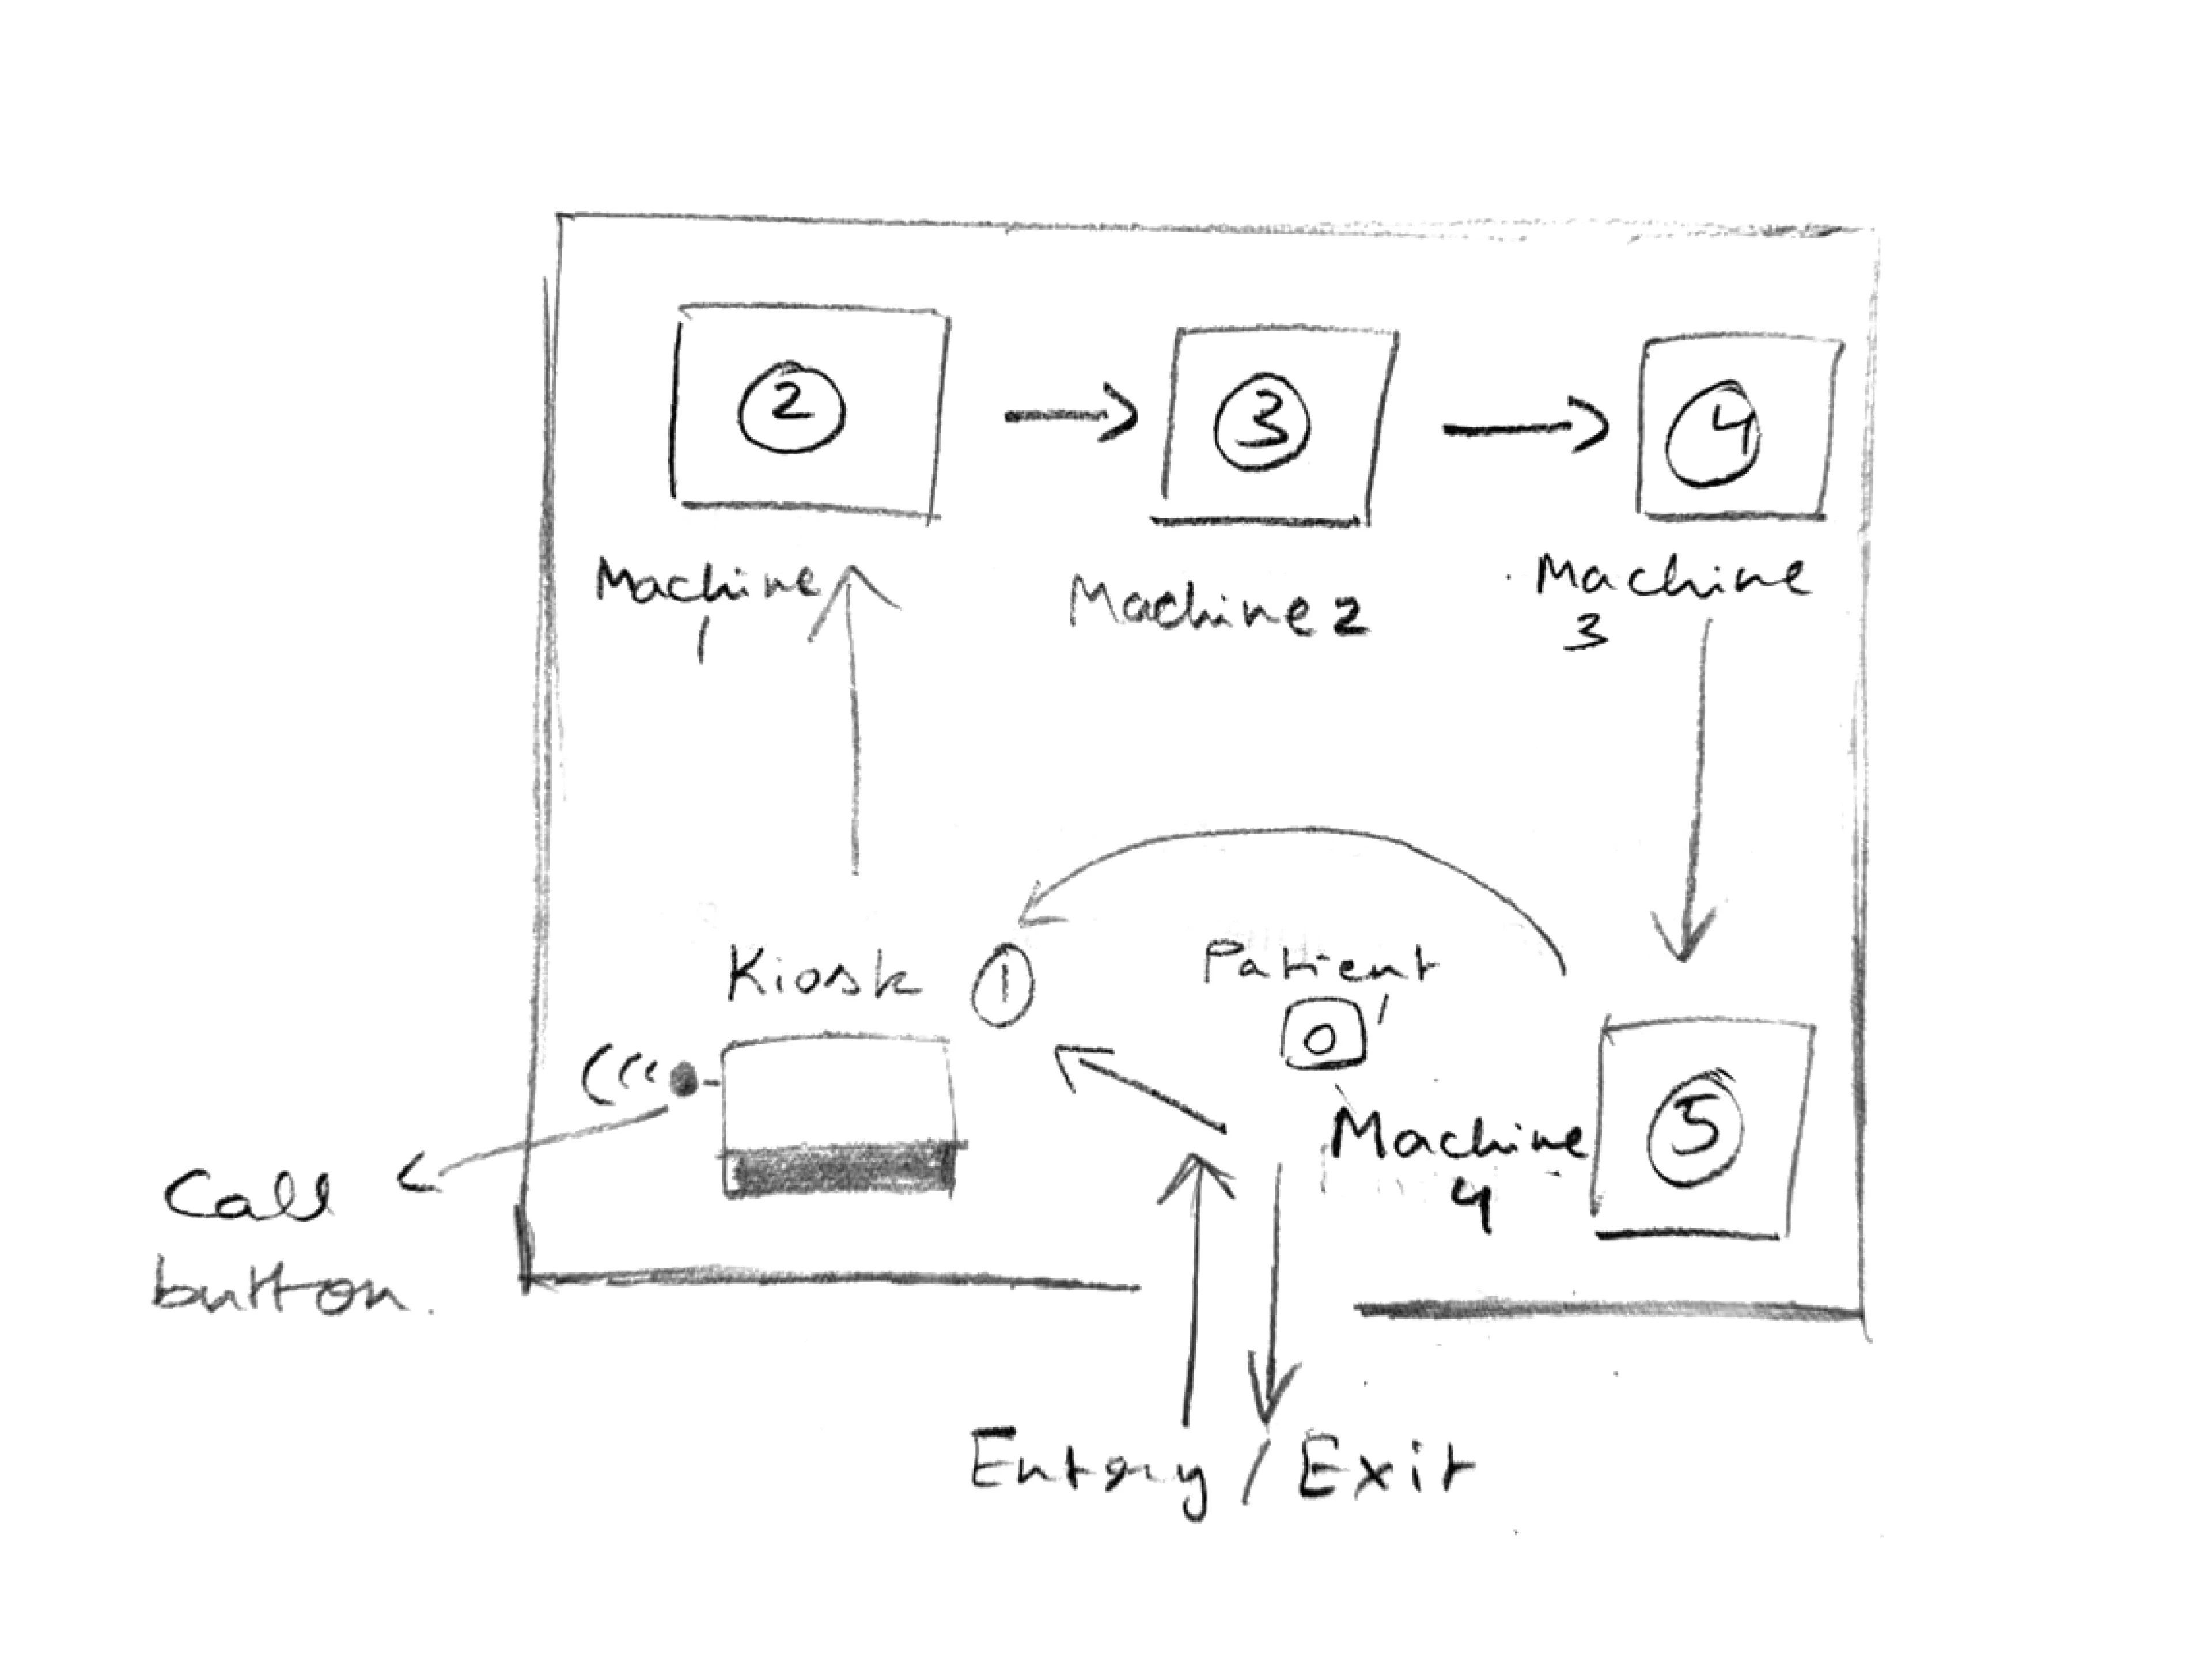
Way-finding booth
Every test in one booth, with signs from machine to machine.
A lot to find your way through, and no one to ask.
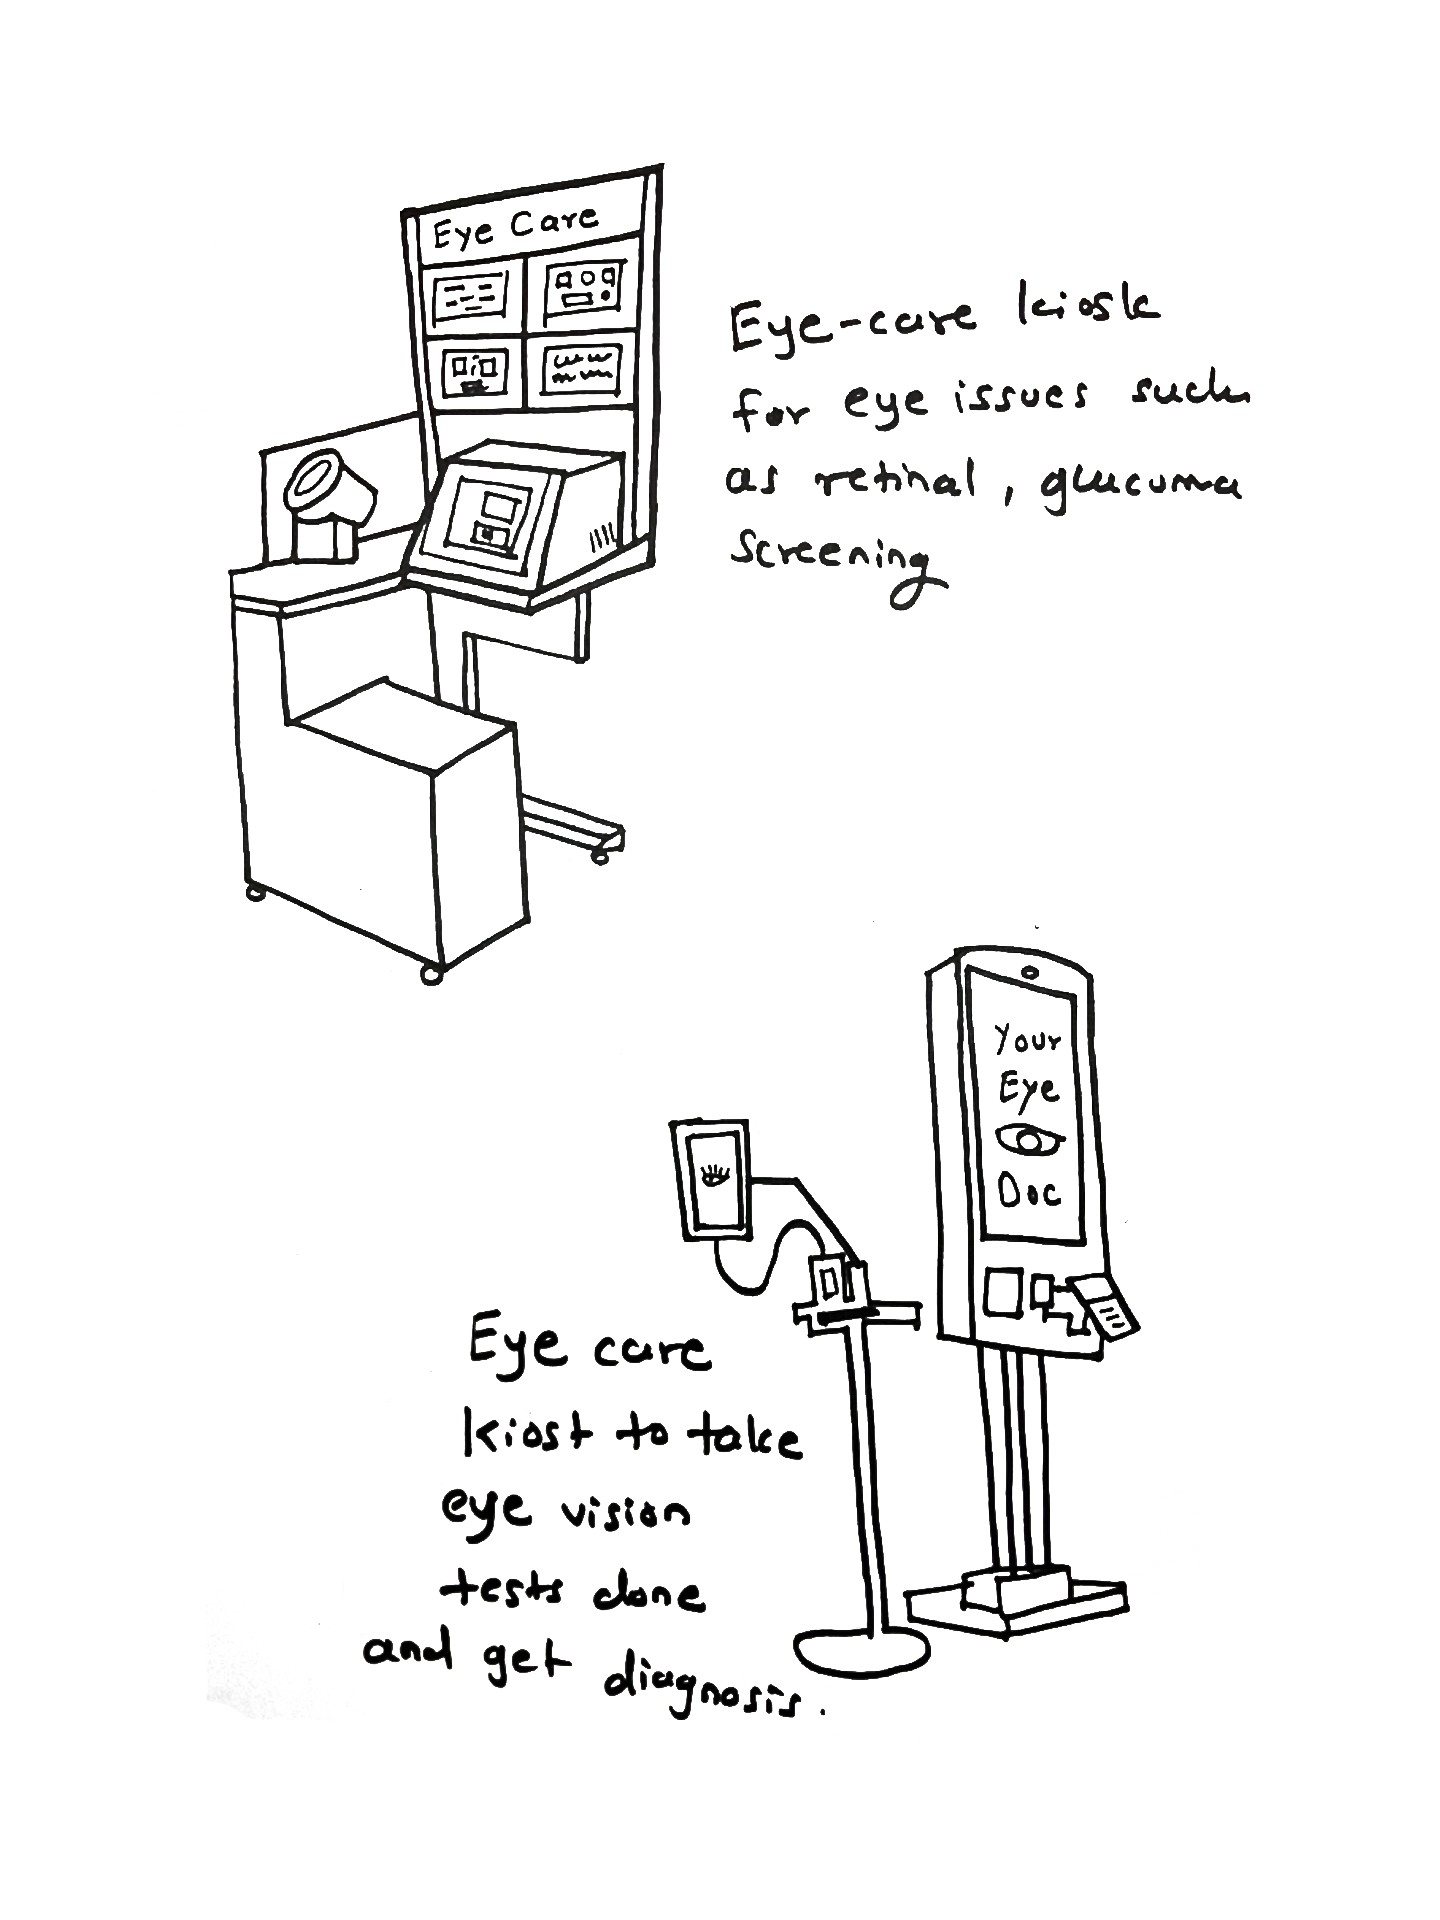
One kiosk, one technician
Local, guided and connected to a specialist.
We took this one forward as Eye Care Connect.
The turn
What changed the project
The answer wasn’t more technology. It was a person.
People didn’t doubt telemedicine because of the camera. They doubted a test with no one beside them. So we put the kiosk where rural patients already go, the pharmacy, and made the pharmacist its technician: someone Bill knows, who runs the test, explains the results and books the specialist.
88.9%
of Americans live within 5 miles of a community pharmacy. In rural areas, most of them are independent or local franchises.
Source: Journal of the American Pharmacists Association, 2022On par
Eye-chart tests run remotely by a trained professional gave the same results as tests in the clinic, in a study of 36 patients.
Source: British and Irish Orthoptic Journal, 2021Bill’s visit, storyboarded
1. Bill needs to see an eye specialist
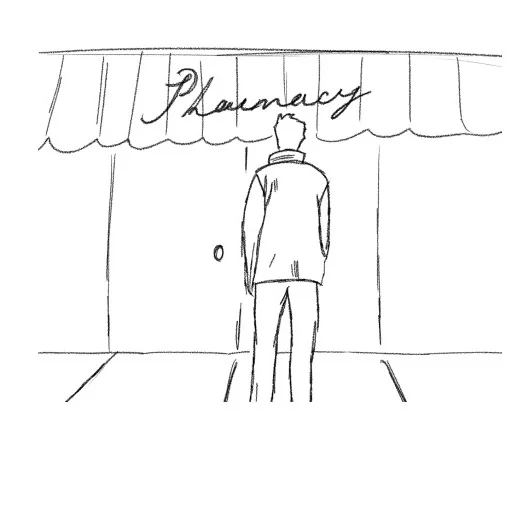
2. He visits his local pharmacy

3. The pharmacist is also the kiosk technician
4. The pharmacist asks a few questions
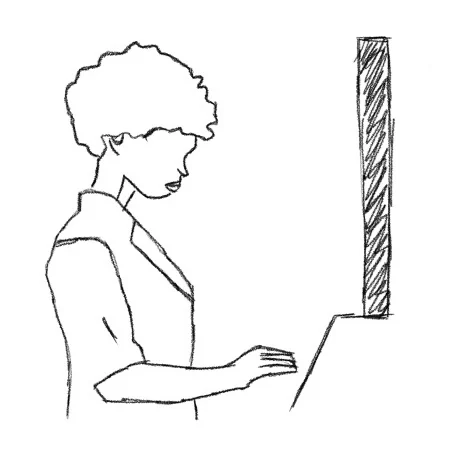
5. and enters his details into the kiosk
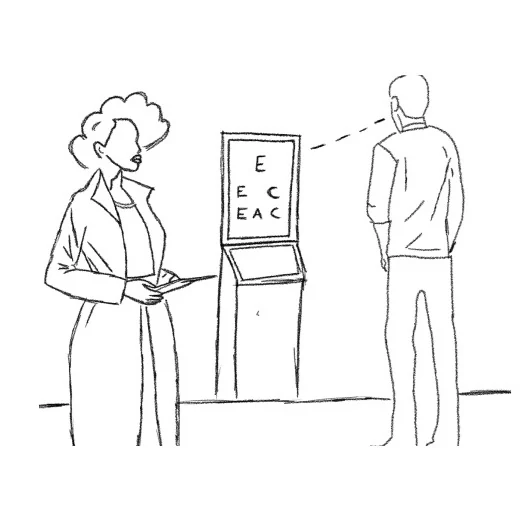
6. The kiosk records his test while the pharmacist watches his progress

7. The kiosk generates his report

8. Either the pharmacist hands Bill his results…

9. …or he meets an eye specialist on video
Bill’s visit
Eye Care Connect is a kiosk in the pharmacy, run by the pharmacist. Four choices shape it, each answering something we heard.
In the pharmacy
Close to home, on a trip Bill already makes.
A person in the loop
The pharmacist guides the test and stands between Bill and the doctor.
Private by design
Dividers around the kiosk keep his health information to himself.
Two ways out
Print the results and go, or book a specialist on the spot.
The kiosk
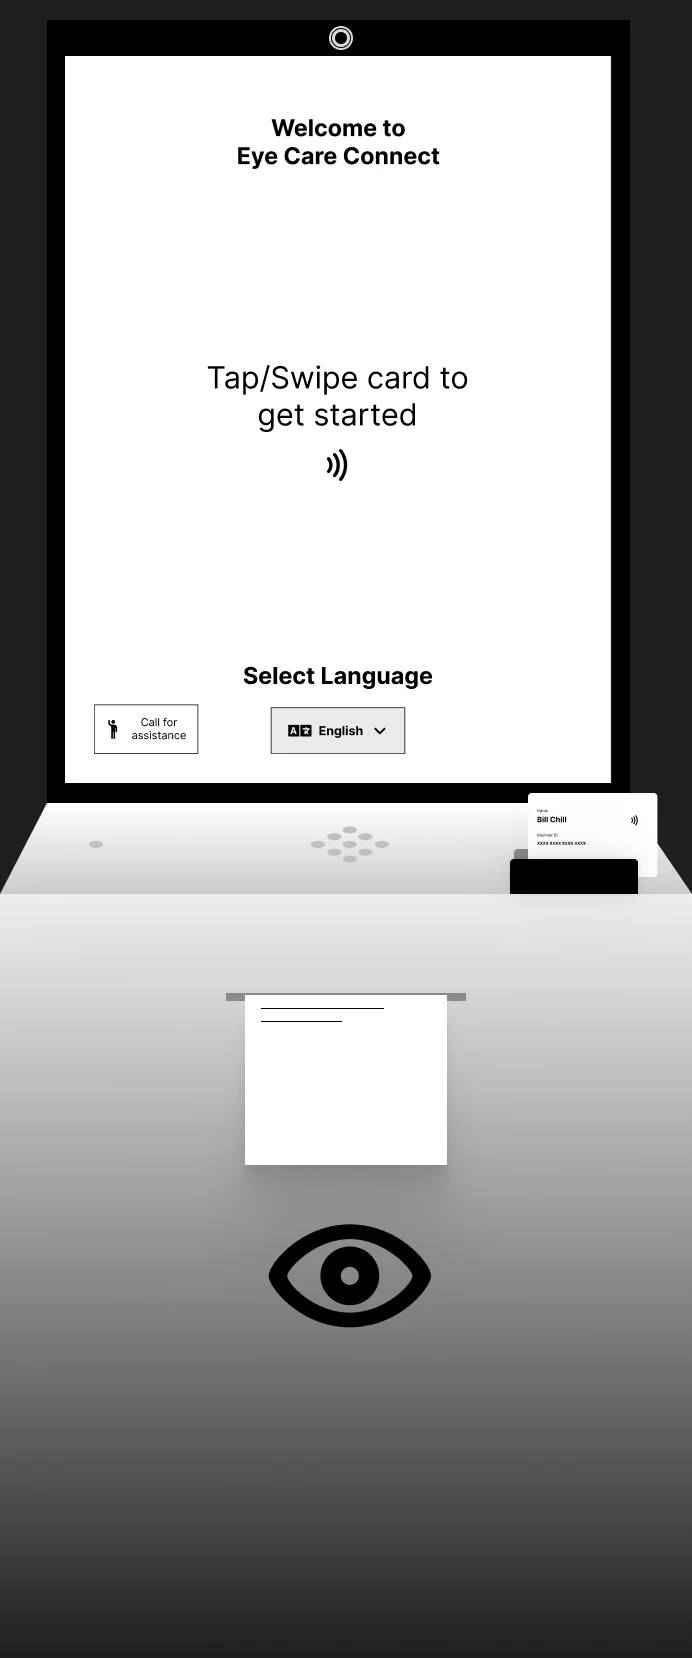
- 1
Camera
For the video call with a specialist
- 2
Call for assistance
Brings the pharmacist over at any step
- 3
Speaker and mic
Instructions read aloud, and a voice for the call
- 4
Card reader
Tap or swipe to pull up his records
- 5
Report printer
He leaves with his results on paper
- 1
Tap in
Bill taps or swipes his card, and the kiosk pulls up his medical information in the language he picks.

- 2
Start the test
A short symptom quiz picks the tests he needs, and the kiosk tells him up front how long they’ll take: about ten minutes.

- 3
Read the chart
His vision is blurry, so the kiosk recommends a visual acuity test, with plain instructions before the chart.

- 4
Results, then a choice
The kiosk analyzes his results and suggests what to do. Bill can print them and leave, or the pharmacist books a video appointment with a partner eye doctor and stays with him for the call.
Either way, he leaves with his results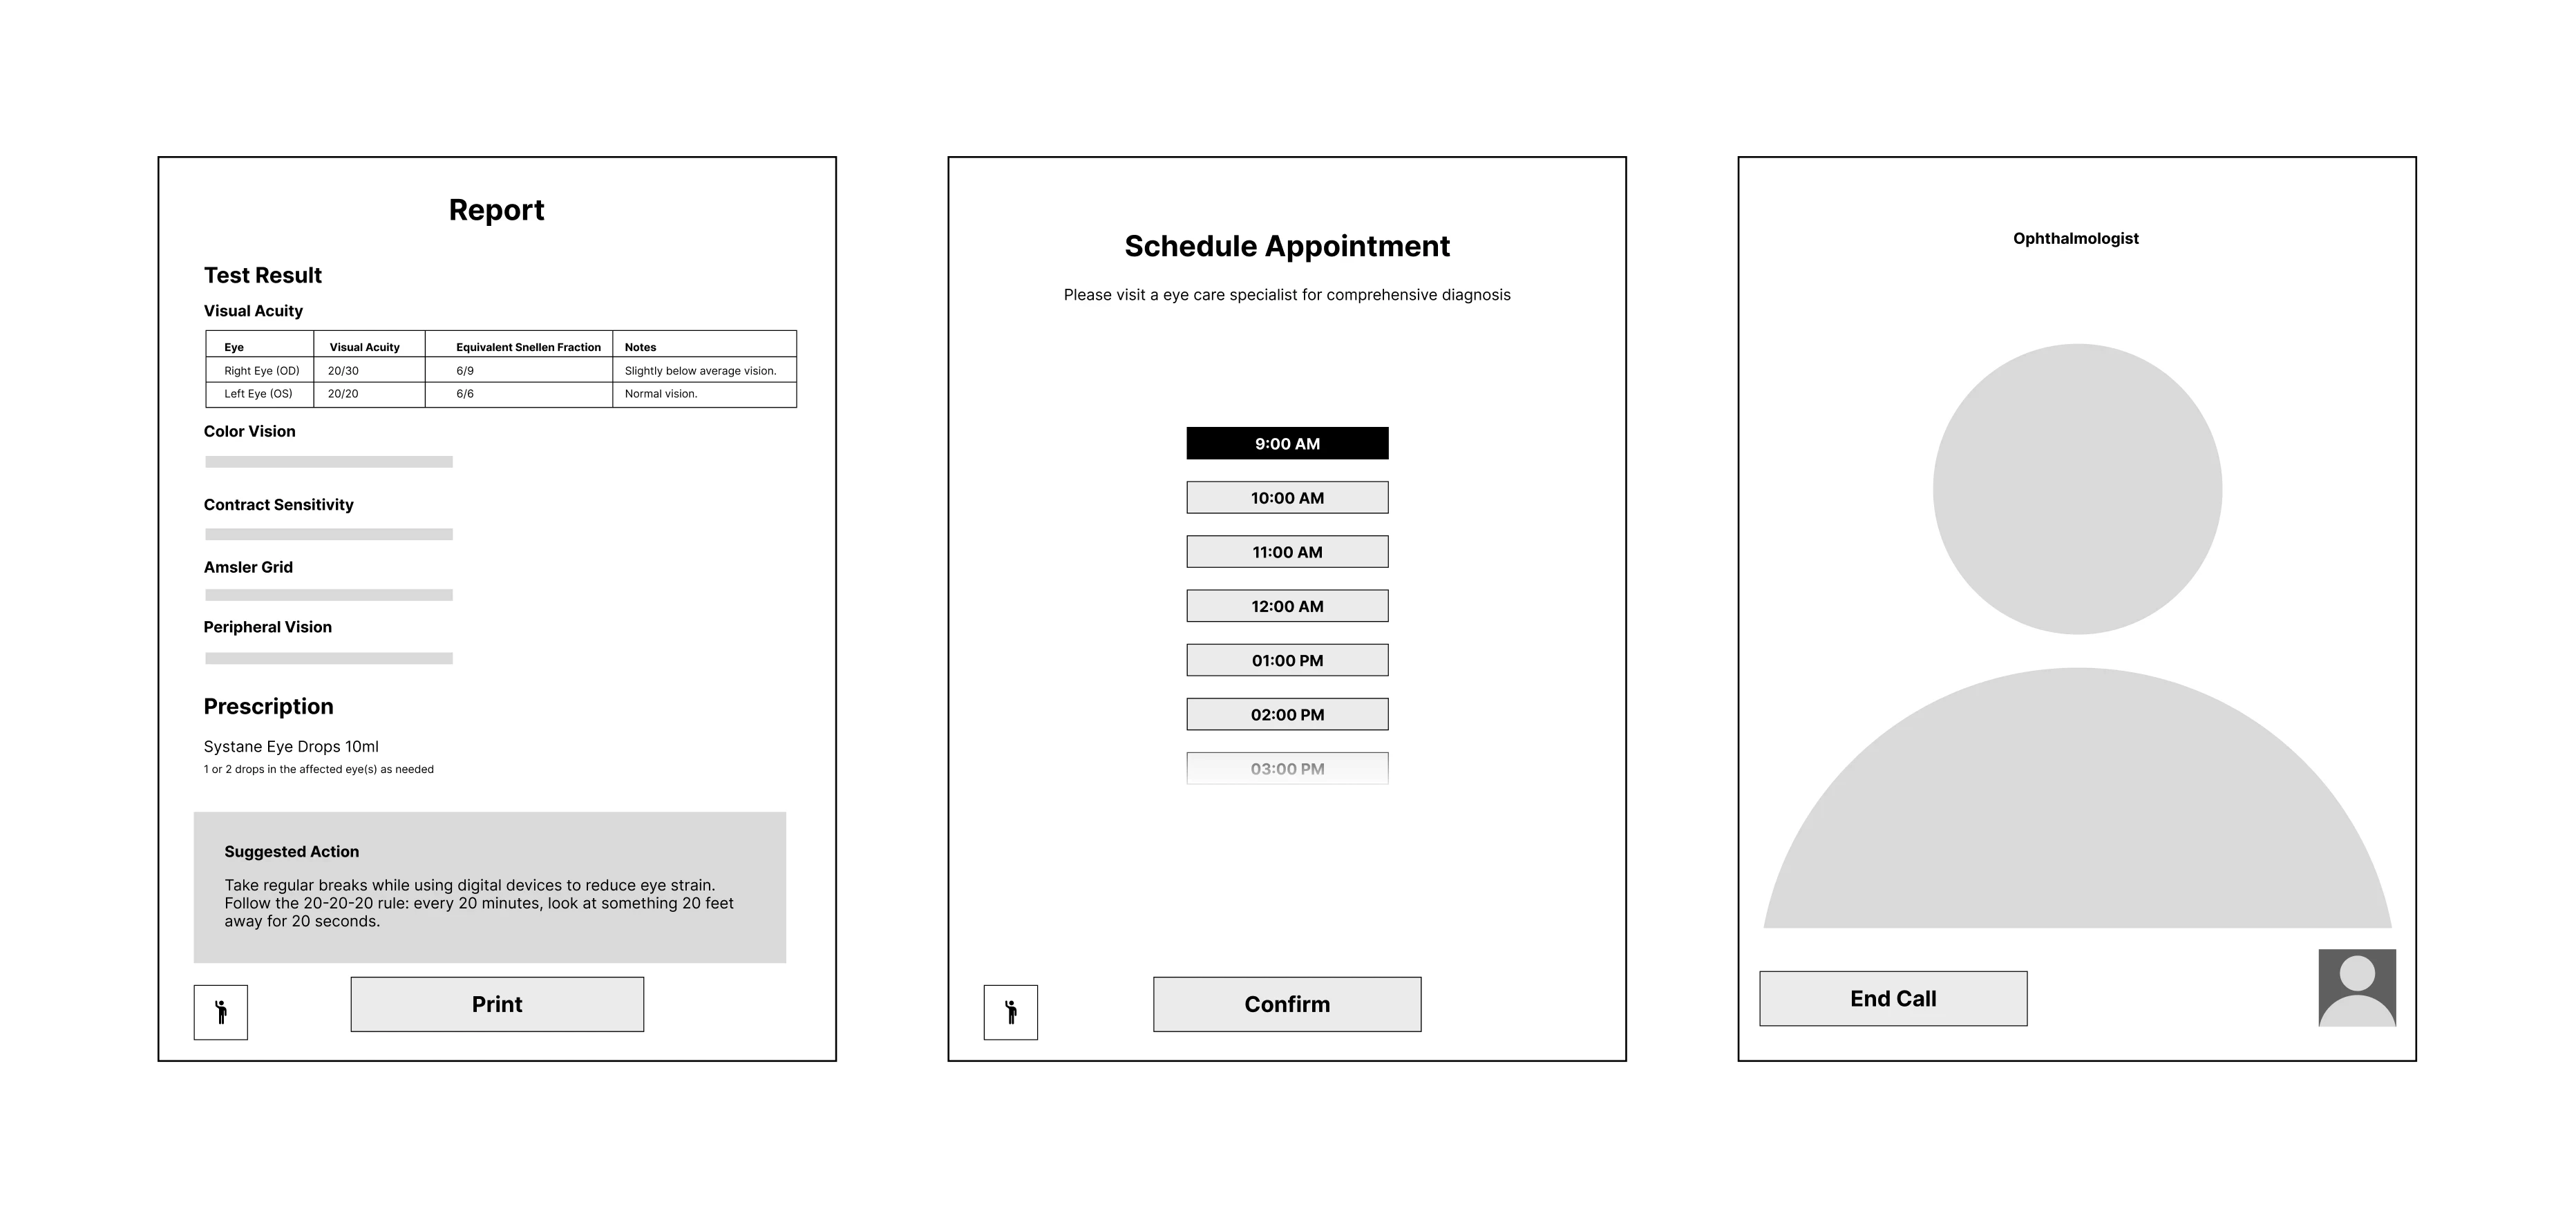

I designed the kiosk’s wireframes, from the welcome screen to the video call, then refined them after testing
Testing it
We tested a prototype of the kiosk on a vertical screen with two participants, watched them read the chart and book an appointment, and asked open questions afterwards.
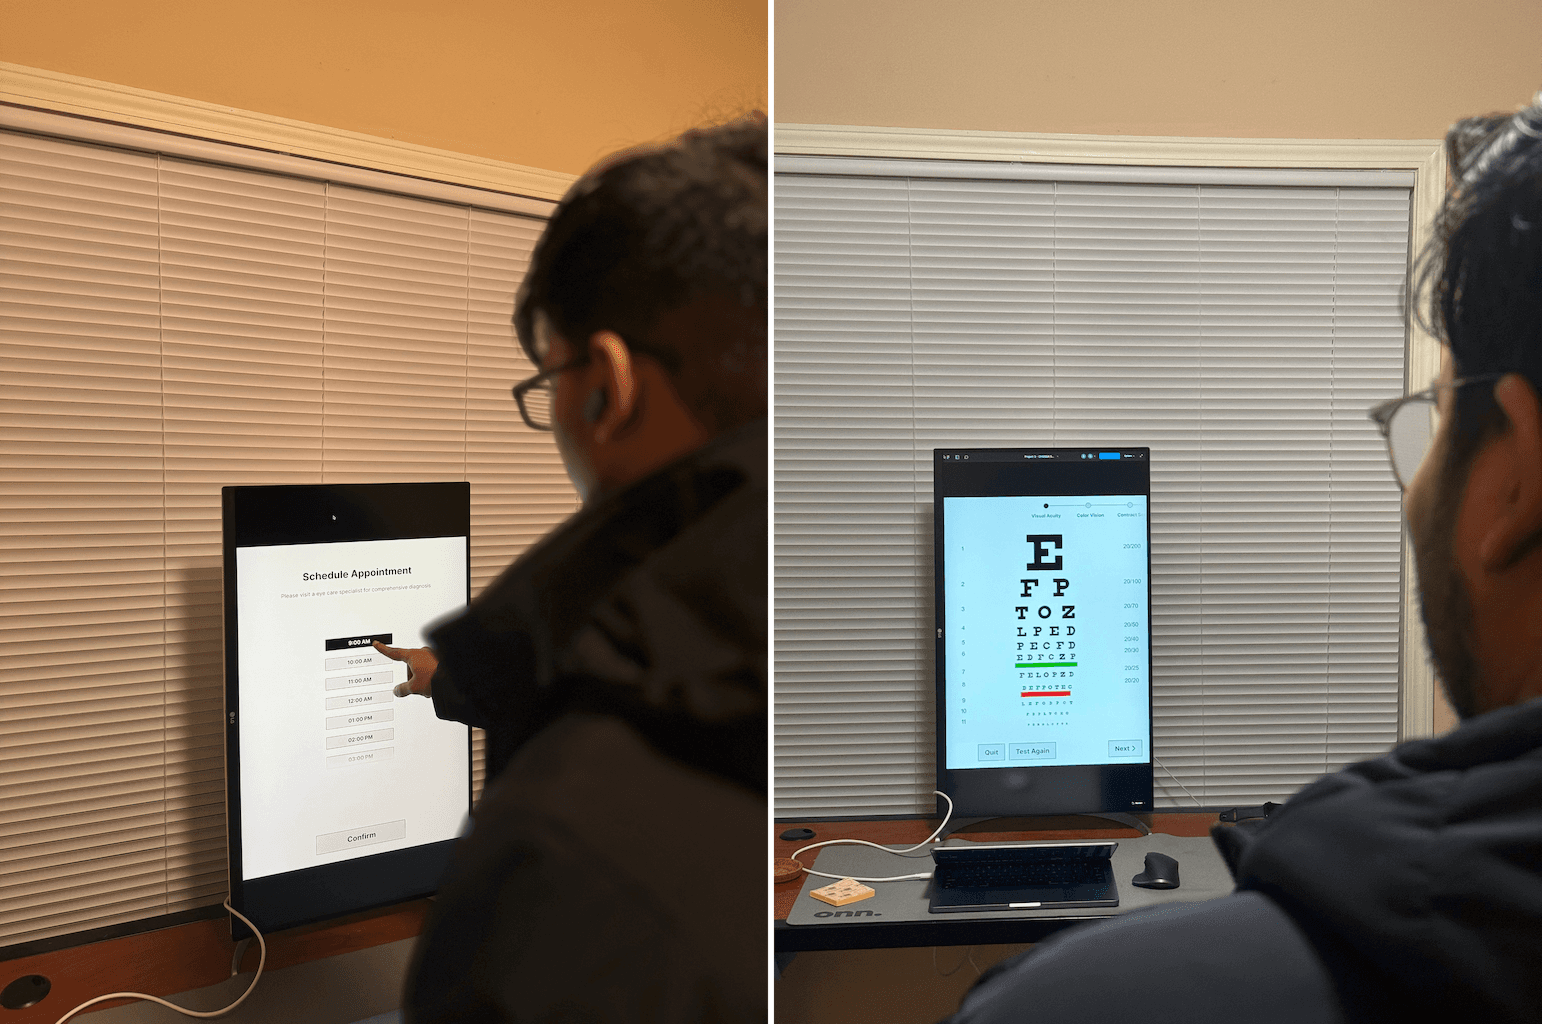
“This can save me a lot of time and the hassle of traveling just to get my eyes checked. This aspect of the kiosk is something I really appreciate.”
“Although I see the benefits of this kiosk, my concern lies with its accuracy. I believe having a trained assistant available to guide users through the process would be immensely beneficial.”
Both valued what the kiosk saves: the trip and the wait. Both also wanted the technician to do more, walking people through each test so the results can be trusted. That was the worry we’d heard in interviews, and it pushed the pharmacist from helper to guide. When we presented in class, the feedback was that installing kiosks could cost a lot, but the benefits seemed worth it.
One honest caveat: our testers were students, not rural patients. The next round has to happen in a rural pharmacy.
Why it holds up
The brief asked for a sustainable answer. Eye Care Connect meets it in four ways.
Care stays local
Eye tests in communities with little access to an eye doctor.
Fewer long drives
Less travel to distant specialists, and the emissions that come with it.
Patients in charge
Bill decides what happens next with his results in hand.
Awareness spreads
A kiosk in the pharmacy puts eye health in front of the whole town.
What I’d carry forward
The fix for trust was a person
Every worry about accuracy, in interviews and in testing, pointed the same way. Putting the pharmacist in the loop answered doubts about the test and about the technology at once.
Meet people where they already go
Most people already live near a pharmacy. Building on a trip Bill already makes asks far less of him than a new one.
Cost is the open question
Class feedback was clear that a kiosk is expensive to install. Working out the cost with a pharmacy partner would decide whether this can exist.
Test with the people who’ll use it
Next, I’d test in a rural pharmacy with real patients, and ask optometrists to check the kiosk’s results against an exam.